Delivery: Protein-delivered base editor preserves...
CMN Briefs
Sep. 11, 2026


For Eric van der Helm, VP Business Development at SNIPR, the case provides an early glimpse of how SNIPR001 might be developed beyond its current focus on preventing infections.
»The treatment hypothesis isn’t new and it didn’t come from this case: our preclinical data already indicated SNIPR001 could be used in a treatment setting, which is why we established an expanded access programme,« he tells CRISPR Medicine News.
SNIPR001 is being clinically developed as an oral treatment to selectively remove E. coli from the intestine and prevent bloodstream infections. Here, physicians instead administered the engineered phages intravenously, topically and directly into an abdominal mass caused by malakoplakia – a rare inflammatory disease associated with persistent E. coli in macrophages.
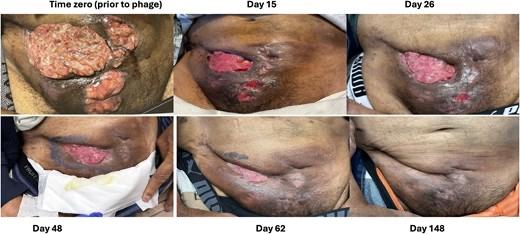
The patient had already undergone multiple courses of antibiotics while the disease continued to worsen and the infecting bacterium acquired further resistance. SNIPR001 was eventually added to a new intensive antibiotic regimen under a single-patient FDA emergency IND. Within a week, large abdominal skin lesions began to heal. The underlying mass subsequently regressed substantially, later urine and tissue cultures were negative, and no adverse events were attributed to the phages.
The improvement cannot be disentangled from the antibiotics and other treatments given alongside SNIPR001. Yet it is notable that the disease had progressed through previous treatment and that the most rapid reduction in the abdominal mass occurred during the period when phage therapy was part of the regimen. It had shrunk by around half after eight weeks and by 89% after one year (see Figure 1).
For SNIPR, the wider implication is therefore not that the case proves efficacy, but that it supports investigating a second way of using a therapy so far developed primarily to act inside the gut.
»This case showed it is feasible to deliver SNIPR001 intravenously, topically and directly into the lesion, and in this single patient the medical team observed no phage-related safety signals,« van der Helm told CRISPR Medicine News. »What it does do is strengthen the case for continuing to develop non-oral delivery for infections that sit outside the gut, for example in tissue or the bloodstream.«
That distinction matters. SNIPR’s Phase 1 trial showed that orally administered SNIPR001 essentially remains in the gastrointestinal tract rather than distributing meaningfully into the circulation or urine. That is an advantage when the aim is precision removal of E. coli from the gut while preserving the wider microbiome, but an infection established in tissue or blood requires another delivery strategy.
The expanded-access case does not establish an appropriate dose or reveal how much active phage reached the infection. It does, however, show that systemic and local administration was feasible in a seriously ill, immunosuppressed patient.
Yesterday's paper in Clinical Infectious Diseases concerns a 65-year-old man who developed recurrent E. coli infections after receiving a kidney transplant in 2023. These eventually culminated in malakoplakia, with an intra-abdominal mass extending through the abdominal wall.
Malakoplakia occurs when macrophages ingest bacteria but fail to kill and digest them efficiently. It is particularly associated with immunosuppression and chronic E. coli infection, making treatment difficult because bacteria may persist in protected intracellular niches.
In this patient, repeated biopsies continued to grow E. coli, the mass enlarged despite multiple antibiotic regimens, and surgery was considered prohibitively risky because of its location near the transplanted kidney and graft vasculature. The bacterium was resistant to several commonly used antibiotics and later became carbapenem-resistant.
“Ultimately only a randomised controlled trial can partition the effect between engineered phage and the other treatments”Eric van der Helm, SNIPR
Before expanded access, SNIPR tested SNIPR001 against the patient’s isolate and found that the cocktail retained strong antibacterial activity in vitro.
SNIPR001 combines four bacteriophages engineered with CRISPR-Cas3 systems programmed to attack essential E. coli DNA. The phages infect susceptible bacteria and deliver the antibacterial CRISPR machinery into the bacterial cell. Preclinical work published in Nature Biotechnology in 2023 showed activity against multidrug-resistant strains and selective reduction of E. coli while largely sparing other tested bacterial species.
The subsequent Phase 1 study published earlier this year in The Lancet Microbe moved that concept into humans. Results showed that oral SNIPR001 was well tolerated in healthy volunteers and demonstrated target engagement with intestinal E. coli without substantially disturbing overall microbiome composition. SNIPR is now developing the oral therapy to prevent E. coli bloodstream infections in patients with haematological malignancies.
The new case extends that story but also illustrates the limitations of expanded-access evidence. When SNIPR001 was introduced, the patient was already receiving tigecycline, meropenem and fosfomycin alongside other treatments. Some antibacterial therapy continued for a year. The improvement could therefore reflect SNIPR001, antibiotics, interactions between the two or other components of treatment.
Nor does the study establish that the CRISPR component was decisive. Although malakoplakia raises the intriguing possibility of reaching E. coli within macrophages, the investigators did not demonstrate that SNIPR001 entered these cells or killed intracellular bacteria. Reduced extracellular bacterial burden, biofilm disruption and phage–antibiotic synergy remain alternative explanations.
»Ultimately only a randomised controlled trial can partition the effect between engineered phage and the other treatments – nothing short of that settles attribution,« van der Helm says. »We’ve been deliberate about not claiming otherwise in the paper.«
The experience nevertheless highlights what future treatment studies need to address. Most importantly, investigators did not measure how much viable SNIPR001 reached the circulation or abdominal mass after intravenous dosing. SNIPR says measuring active phage at the infection site would be a priority in a prospective protocol.
Future studies would also ideally bank bacterial isolates at fixed time points to monitor phage susceptibility and resistance. In this case, later cultures were negative – clinically the desired result, but one that left no post-treatment isolates to analyse.
“Prevention and treatment are structurally different businesses”Eric van der Helm, SNIPR
SNIPR’s immediate development priority remains prevention. Recruitment is complete in a randomised Phase 1b/2a trial of oral SNIPR001 in 24 patients with haematological cancer across eight US centres, and the programme has FDA Fast Track designation for prevention of bloodstream E. coli infections in patients at risk of neutropenia.
Treatment is not, however, an idea generated by this case. SNIPR says its preclinical findings had already supported the hypothesis, prompting it to establish an expanded-access programme. The company regards this as a humanitarian route rather than an alternative to formal clinical development. Physician requests through the emergency IND pathway indicate unmet need, but not efficacy.
If SNIPR eventually pursues active infection as an indication, it could also substantially broaden the commercial opportunity.
»Prevention and treatment are structurally different businesses: prophylaxis serves a defined, identifiable at-risk population on scheduled oral dosing, whereas treatment means a larger, heterogeneous, acute hospital population, with different customers, settings and economics,« van der Helm says.
Possible indications include urinary tract infections, sepsis and infections in transplant recipients, but each would require a dedicated clinical programme establishing efficacy, dosing and delivery.
For now, the case supports a narrower but important conclusion. SNIPR001, developed to act selectively in the gut, was deployed in fundamentally different ways in a patient whose disease had resisted conventional management – and its addition was followed by an exceptional clinical response. Whether the engineered phages contributed materially to that response, and whether it can be reproduced in other patients, are now questions for controlled clinical trials.
The study was performed by Saima Aslam and colleagues at the University of California San Diego and SNIPR, Copenhagen. It was published in Clinical Infectious Diseases on 11 August 2026. The phase 1 clinical results were published in The Lancet Microbe on 2 March 2026. The preclinical characterisation of SNIPR001 was published in Nature Biotechnology in 2023.
To get more CRISPR Medicine News delivered to your inbox, sign up to the free weekly CMN Newsletter here.
ArticleInterviewNewsStickyClinical News UpdatesIn vivoBacterial diseasesInfectious diseases - otherBacterial InfectionCas3SNIPR BiomeClinicalIND - Investigational New Drug